Bioceuticals.AI
Evidence

Early evidence in two cancers

These results are retrospective analyses of public datasets. They are labelled clearly as preliminary and are not evidence of clinical efficacy.

All figures below are derived from datasets in GEO and TCGA using the Pairwise RNA Co-expression Analysis (PRCA) method and the RNA QR code representation.

RETROSPECTIVE · PUBLIC DATA (GEO/TCGA) · PRELIMINARY
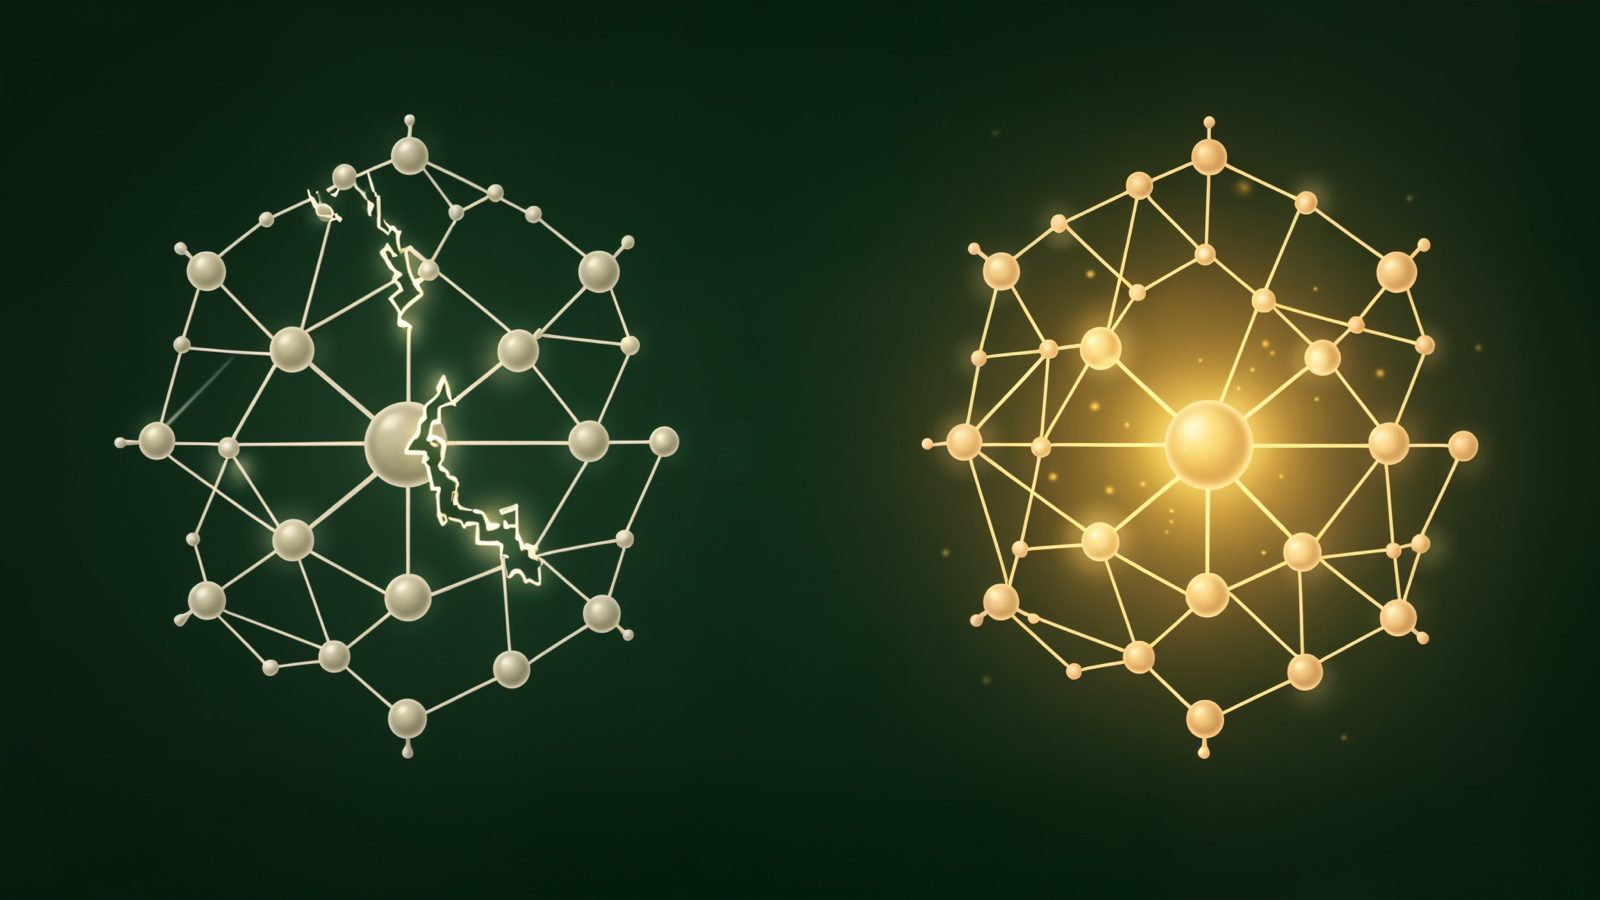
Illustration: a disrupted gene network beside a restored one
Illustration of the two states the indices measure: disrupted (left) and restored (right). Figures on this page: RETROSPECTIVE · PUBLIC DATA (GEO/TCGA) · PRELIMINARY.
Breast cancer · doxorubicin

RNA QR codes stratify survival

In a retrospective analysis of public GEO data, pre-treatment RNA QR codes from breast-cancer patients receiving doxorubicin separated long from short survivors.

~10 months vs ~7 weeks

Approximate survival separation between long- and short-survival QR-code patterns.

69%

Restoration Index: 92 of 134 disrupted genes restored under doxorubicin.

Source: public breast-cancer transcriptome data (GEO). Retrospective only; not a prospective trial and not a clinical-utility study.

Interpretation

The breast-cancer analysis shows that the TI/RI framework can detect network-level differences in pre-treatment samples and quantify how far a cytotoxic drug restores disrupted modules.

The result suggests that network fingerprints contain prognostic information that single-gene markers may miss, and that RI can summarise a complex transcriptomic response as a single systems-level score.

Prostate cancer · androgen therapy

Quantifying disruption and restoration

In TCGA prostate-cancer data, the RNA QR code and its scores quantify both how much the tumor state disrupts healthy modules and how much androgen therapy restores them.

22%

Disruption Index: 5 of 23 healthy modules lost in the tumor state.

54%

Restoration Index for androgen therapy in the expanded cohort.

Source: TCGA prostate-cancer transcriptome data. Initial small-sample analysis suggested 0% restoration; the larger dataset refined this to 54%.

Interpretation

The prostate-cancer analysis illustrates how TI and RI can be read together: TI captures baseline network damage; RI captures how much a specific therapy counteracts it.

Because both metrics are derived from the same modules, they can be compared across drugs, doses and patient subgroups, and extended to autoimmune and CNS indications where similar data exist.

Limitations

What these figures do and do not show

  • The analyses use existing public data only; no new patients were enrolled and no new biopsies were taken.
  • The endpoints are transcriptomic: disruption and restoration of gene modules, not clinical response.
  • The work has not yet been prospectively validated in pre-registered trials or used to change patient care.
  • The figures are provided to illustrate how the method behaves on real data, not to make treatment claims.

Next steps

The next planned evidence comes from three pre-registered analyses of EBV-related disease, all run on public datasets with success criteria fixed in advance. Those plans are described on the EBV program page.

Any future clinical use would require additional validation, regulatory review and collaboration with treating physicians.